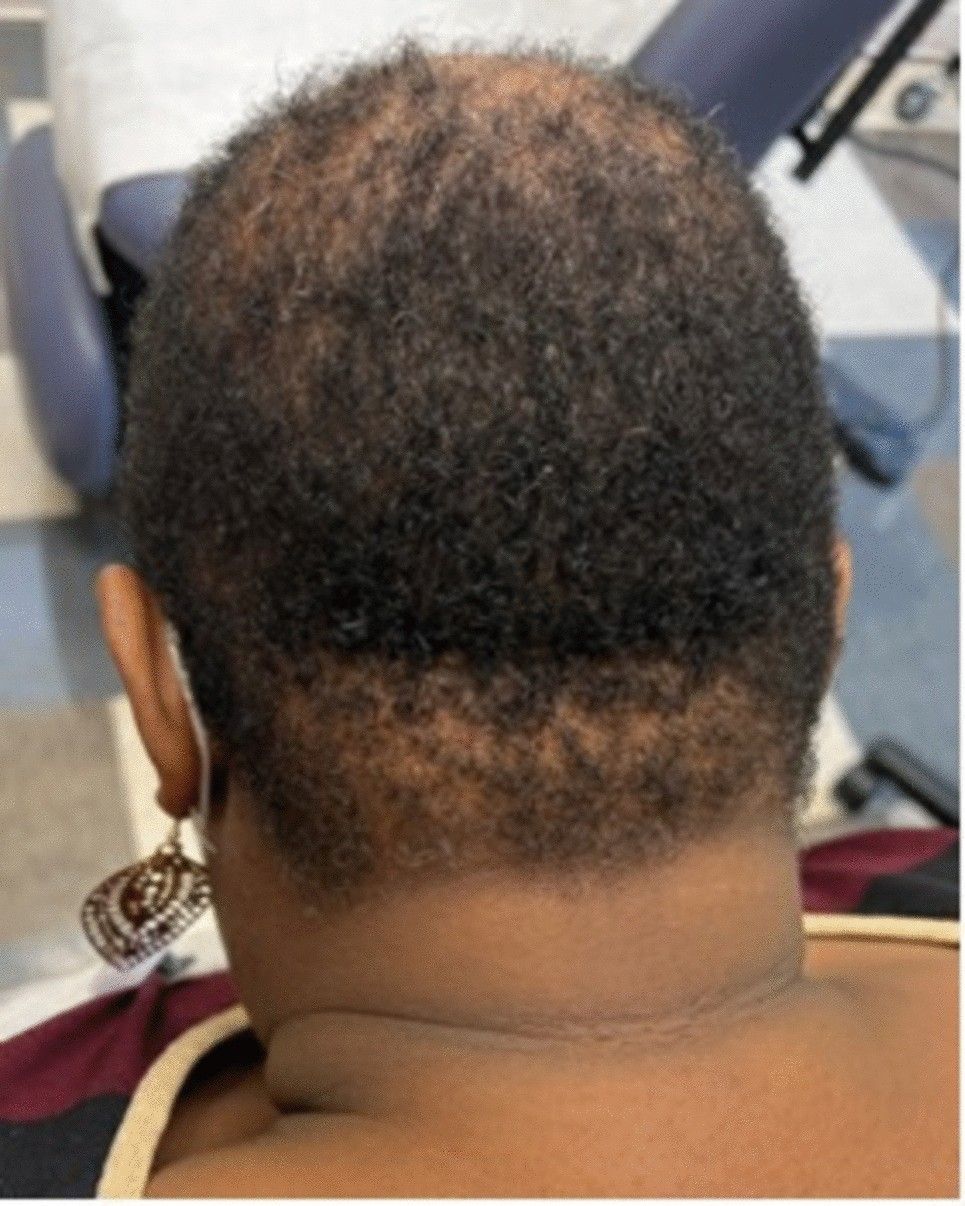
Hormones and female hair loss
Hormonal changes can contribute to female hair loss, but the pattern and medical history determine which investigations may be useful.


Which hormones drive female hair loss?
The hair follicle is one of the most hormonally sensitive structures in the body. Each follicle cycles through three phases: anagen (active growth), catagen (transition), and telogen (shedding). Hormones determine how long each phase lasts, which directly controls hair density and thickness.
The key hormones involved are:
- Oestrogen promotes the anagen phase, keeping hair in active growth for longer. When oestrogen levels fall, follicles spend more time in telogen, producing noticeable thinning. Oestrogen and hair thinning are closely linked, particularly during perimenopause and menopause.
- DHT (dihydrotestosterone) is converted from testosterone by the enzyme 5-alpha reductase. The role of DHT in hair loss is to bind to androgen receptors in follicles, causing them to shrink progressively. This process, called follicle miniaturisation, is the defining mechanism of female pattern hair loss (androgenetic alopecia).
- Progesterone naturally inhibits 5-alpha reductase, reducing DHT conversion. When progesterone declines, this protective effect weakens and androgen activity at the follicle increases.
- Cortisol , the primary stress hormone, triggers telogen effluvium. Elevated cortisol levels push large numbers of follicles into the shedding phase simultaneously, causing diffuse hair loss that typically appears two to three months after a stressful event.
- Thyroid hormones (T3 and T4) regulate the metabolic rate of every cell, including follicle cells. Both hypothyroidism and hyperthyroidism disrupt the hair cycle, producing brittle, thinning hair and increased shedding.
Describe the pattern and timing of shedding to your GP. Your history and examination will help determine whether blood tests are needed and which tests would be useful.
The effects of hormones on hair are rarely isolated. Most women experiencing significant hair loss have more than one hormonal factor at play simultaneously.
How do life stages and medical conditions cause hormonal hair loss?
Hormonal imbalance hair loss does not occur randomly. It follows predictable patterns tied to specific life events and underlying health conditions.
-
Menopause and perimenopause. Declining oestrogen and progesterone relative to androgen activity is the central driver of hair loss due to menopause. A 2026 survey of nearly 6,000 women found that 50% reported hair thinning during perimenopause and menopause. That figure confirms hair thinning is not a minor side effect of this life stage. It is a widespread physiological consequence of hormonal change. Elevated Luteinising Hormone (LH) during menopause adds a further complication. LH can accelerate follicle ageing independently of androgens, triggering oxidative stress and cellular senescence in follicles. This means hair loss in menopausal women has at least two distinct hormonal pathways operating at once.
-
Polycystic ovary syndrome (PCOS). PCOS is the most common endocrine disorder in women of reproductive age. Approximately 70% of women with PCOS exhibit insulin resistance, which lowers sex hormone-binding globulin (SHBG) and raises free testosterone. More free testosterone means more DHT conversion and faster follicle miniaturisation.
-
Metabolic syndrome. The connection between metabolic health and hair is frequently overlooked. Research shows that 59.4% of women with female pattern hair loss have metabolic syndrome. Insulin resistance, elevated triglycerides, and central obesity all alter androgen metabolism in ways that accelerate hair thinning.
-
Thyroid disease. Both an underactive and overactive thyroid disrupt the hair cycle. Thyroid hormones and hair health are directly connected because follicle cells require stable T3 and T4 levels to maintain normal cycling. Thyroid-related hair loss often presents as generalised thinning across the entire scalp rather than patterned loss.
Tell your GP about any thyroid condition and other symptoms. Ask whether further investigation, including iron status where appropriate, would help explain the hair loss.
Female hair loss rarely results from a single cause. Nutritional deficiencies, hormonal shifts, and lifestyle factors typically overlap, which is why addressing only one factor often produces limited results.
What diagnostic approaches identify hormonal hair loss?
Accurate diagnosis separates hormonal hair loss from other causes and prevents ineffective treatment. UK specialists use a combination of clinical and laboratory methods.
Clinical examination tools:
- Dermoscopy allows a specialist to examine follicle diameter and density at the scalp surface. It can identify miniaturised follicles characteristic of androgenetic alopecia before hair loss becomes visually obvious.
- The pull test assesses active shedding. A positive result, where more than six hairs are removed with gentle traction, indicates telogen effluvium or another active shedding condition.
Blood tests to request:
Hormones and female hair loss: what the evidence shows
By Dr Harpreet Kalra · Updated 30 August 2026 · 7 minute read

Hormonal changes can affect the hair-growth cycle, but they are not the only explanation for hair loss in women. Genetics, illness, iron deficiency, medicines, weight loss, stress and inflammatory scalp conditions can all produce thinning or shedding. The pattern and speed of the change are often more informative than assuming one hormone is responsible.
Female pattern hair loss is the most common form of hair loss in women. It usually develops gradually, with a wider central parting and reduced density over the top of the scalp while the frontal hairline often remains in place. The British Association of Dermatologists describes both genetic and hormonal factors, although many affected women do not have raised androgen levels.
How hormones fit into female hair loss
Each follicle moves through growth, transition and resting phases. A major physical change can move more follicles than usual into the resting phase, leading to diffuse shedding several months later. This is called telogen effluvium. It differs from the gradual follicle miniaturisation seen in female pattern hair loss.
Hormones are particularly relevant when hair loss appears alongside other changes:
- Polycystic ovary syndrome (PCOS): female pattern hair loss can occur with androgen excess. Irregular periods, acne, increased facial or body hair and difficulty becoming pregnant are reasons to speak to a GP.
- Perimenopause and menopause: thinning is more common in later life, but age, genetics, health and medicines can overlap. Menopause should not be assumed to be the sole cause.
- Thyroid disease: both an underactive and an overactive thyroid can be associated with diffuse loss. Thyroid testing is useful when the history or other symptoms suggest it.
- Pregnancy and childbirth: increased shedding often begins after childbirth. This is usually telogen effluvium and commonly improves as the hair cycle settles.
- Changes to medicines: some medicines and changes to hormonal treatment can alter shedding. Ask the prescriber to review the timing rather than stopping a medicine without advice.
Stressful events can also trigger telogen effluvium. This does not make cortisol the routine first test, nor does stress explain every case of diffuse loss. The medical history and scalp examination come first.
The pattern and pace of change matter
Gradual thinning through the central parting or crown, with a normal-looking scalp, is typical of female pattern hair loss. Telogen effluvium tends to cause a more sudden increase in shedding from across the scalp, often around three months after illness, surgery, childbirth, marked weight loss or another major physical or emotional stress.
Smooth round patches may indicate alopecia areata. Redness, scale, pain, burning, a smooth or shiny area, eyebrow loss or recession in a band around the frontal hairline can point to another condition that needs medical assessment. The clinic's guide to types of alopecia explains why patchy, diffuse and scarring patterns are assessed differently.
Which blood tests may be useful?
There is no single female hair-loss panel that everyone needs. Diagnosis begins with the duration and pattern of loss, recent health changes, menstrual history, medicines, diet, family history and examination of the scalp.
NICE advises considering thyroid function, a full blood count, ferritin and vitamin D, particularly when telogen effluvium is suspected. Tests for androgen excess may be appropriate when hair loss occurs with irregular periods, acne, increased facial hair or other features of PCOS. Dermoscopy and, less commonly, a scalp biopsy may be needed when examination does not give a clear diagnosis.
Ferritin has no universal hair-growth target
Ferritin is used to assess iron stores, and iron deficiency can contribute to diffuse shedding. Claims that every patient needs a ferritin result of 70 or 100 micrograms per litre for hair growth are not based on an agreed clinical threshold. Results must be interpreted with the laboratory range, full blood count, symptoms and factors such as inflammation, which can raise ferritin.
Do not start iron supplements solely because of an online hair-loss target. A GP can confirm whether iron deficiency is present, investigate its cause and advise on treatment.
Treatment follows the diagnosis
When shedding is linked to illness, iron deficiency, thyroid disease, a medicine or another identifiable trigger, treatment focuses on that cause. Telogen effluvium usually improves without a hair-growth medicine, although it can take months for the previous volume to return.
Topical minoxidil may slow female pattern hair loss and produce partial regrowth in some women. It usually needs at least six months before benefit can be judged, and any benefit lasts only while treatment continues. Scalp irritation and a temporary increase in shedding can occur.
Topical minoxidil should not be used during pregnancy or while breastfeeding. The British Association of Dermatologists also advises avoiding it when planning a pregnancy. If you become pregnant while using minoxidil, stop using it and contact your GP or pharmacist for advice.
A dermatologist may sometimes consider low-dose oral minoxidil or an anti-androgen such as spironolactone. These medicines are not licensed for female pattern hair loss in the UK and require individual assessment, monitoring and specific pregnancy precautions. HRT may be prescribed for appropriate menopause symptoms, but it is not a hair-loss treatment and should not be started simply in the hope of reversing thinning.
Wigs, hairpieces and fibre products can provide useful camouflage. Evidence for platelet-rich plasma remains limited, and it should not be presented as a guaranteed way to restart growth. Hair transplantation is considered only for selected women with permanent, stable loss and a suitable donor area. The clinic's hair transplant guide for women explains how suitability and donor supply are assessed.
When to speak to your GP
Arrange a GP appointment if hair loss is sudden, patchy, painful or inflamed, or appears with fatigue, unexplained weight change, irregular periods, increased facial hair or eyebrow loss. Seek advice as well if shedding persists, the scalp is becoming more visible or the change is affecting your wellbeing. NHS guidance recommends establishing the cause before approaching a commercial hair clinic.
The clinic's hair loss advice hub has more information on common patterns and assessment.
Questions and answers
Do normal hormone blood tests rule out female pattern hair loss?
No. Female pattern hair loss can occur without an abnormal result on a routine hormone test. Diagnosis considers the pattern of thinning, scalp examination and medical history.
Does everyone with thinning hair need the same blood tests?
No. Tests should be chosen according to the symptoms and examination. Mention menstrual changes, recent pregnancy, weight changes and medicines so the clinician can decide what is relevant.
Should I start hormone treatment to improve my hair?
Do not start or change hormone treatment on the basis of hair thinning alone. Discuss the cause of the loss and the potential benefits and risks of any treatment with your clinician.
Dr Harpreet Kalra
Newcastle Hair Transplant Clinic