Causes of hair loss in men
Gradual thinning, sudden shedding and patchy loss can have different causes. The pattern and timing help guide assessment.


Common reversible causes include:
- Telogen effluvium (triggered by illness, stress, surgery, or rapid weight loss)
- Nutritional deficiencies such as low iron or zinc
- Scalp infections or inflammatory skin conditions
- Certain medications, including some blood pressure drugs and antidepressants
Hair loss that causes distress, regardless of its cause, is also a valid reason to speak to a GP. You do not need to wait until it becomes severe.
- What are the most common hair loss causes in men?
- How does a GP diagnose hair loss, and when should you seek help?
- Is your hair loss temporary or permanent?
- What treatments are available for male hair loss in the UK?
- Practical steps to protect your hair and scalp
- UK resources and how to check a clinic’s credentials
- Useful sources
- FAQ
What are the most common hair loss causes in men?
Understanding why your hair is thinning starts with recognising the pattern. Different causes produce distinctly different presentations, and that pattern is often the most useful diagnostic clue a clinician has.
| Cause type | Pattern/location | Reversibility | Clinician tests/questions |
|---|---|---|---|
| Androgenetic alopecia (genetic) | Receding hairline, crown thinning | Permanent (manageable) | Family history, scalp exam |
| Telogen effluvium (temporary) | Diffuse shedding across the scalp | Usually temporary | Recent illness, stress, weight change, ferritin |
| Alopecia areata (autoimmune) | Discrete smooth patches | Variable; may remit or relapse | Scalp exam, autoimmune screen if indicated |
| Traction alopecia (mechanical) | Hairline and temples, linked to tight styles | Often reversible if caught early | Hairstyle history |
| Medical/systemic causes | Diffuse or patchy, may include beard/brows | Depends on underlying condition | Thyroid function, medication review |
| Scalp conditions | Variable; often diffuse with scaling or inflammation | Usually reversible | Scalp exam, dermatology referral if needed |
| Nutritional deficiency | Diffuse shedding | Reversible with correction | Ferritin, zinc, Vitamin D |
Androgenetic alopecia
This is the cause most men are dealing with. Dihydrotestosterone (DHT) acts on genetically susceptible follicles, shortening the growth phase and causing progressive miniaturisation until the follicle stops producing visible hair. The typical pattern begins with a receding hairline at the temples, followed by thinning at the crown. Crucially, many genes influence when and how severely this occurs, which is why the pattern varies so widely between men even within the same family. Most men with androgenetic alopecia have entirely normal blood hormone levels; the issue is local follicle sensitivity to DHT, not systemic hormonal excess. Loss is permanent without treatment, though it can be slowed significantly. For a detailed look at genetic factors in baldness, the hereditary picture is more complex than most men realise.
Telogen effluvium
Telogen effluvium is the second most common cause and is frequently misidentified as pattern baldness. It produces diffuse shedding across the whole scalp rather than a defined pattern. Triggers include illness, significant stress, chemotherapy, weight loss, and iron or zinc deficiency. The shedding typically begins two to four months after the triggering event, which is why men often struggle to identify the cause. In most cases, hair regrows fully once the trigger is resolved, though this can take six to twelve months.
Alopecia areata
Alopecia areata is an autoimmune condition that causes discrete, smooth, coin-shaped patches of hair loss. It can affect the scalp, beard, and eyebrows. Prognosis is unpredictable; some men experience a single episode with full regrowth, while others have a relapsing course. Extensive or rapidly progressing alopecia areata warrants dermatology referral.
Traction alopecia and scalp conditions
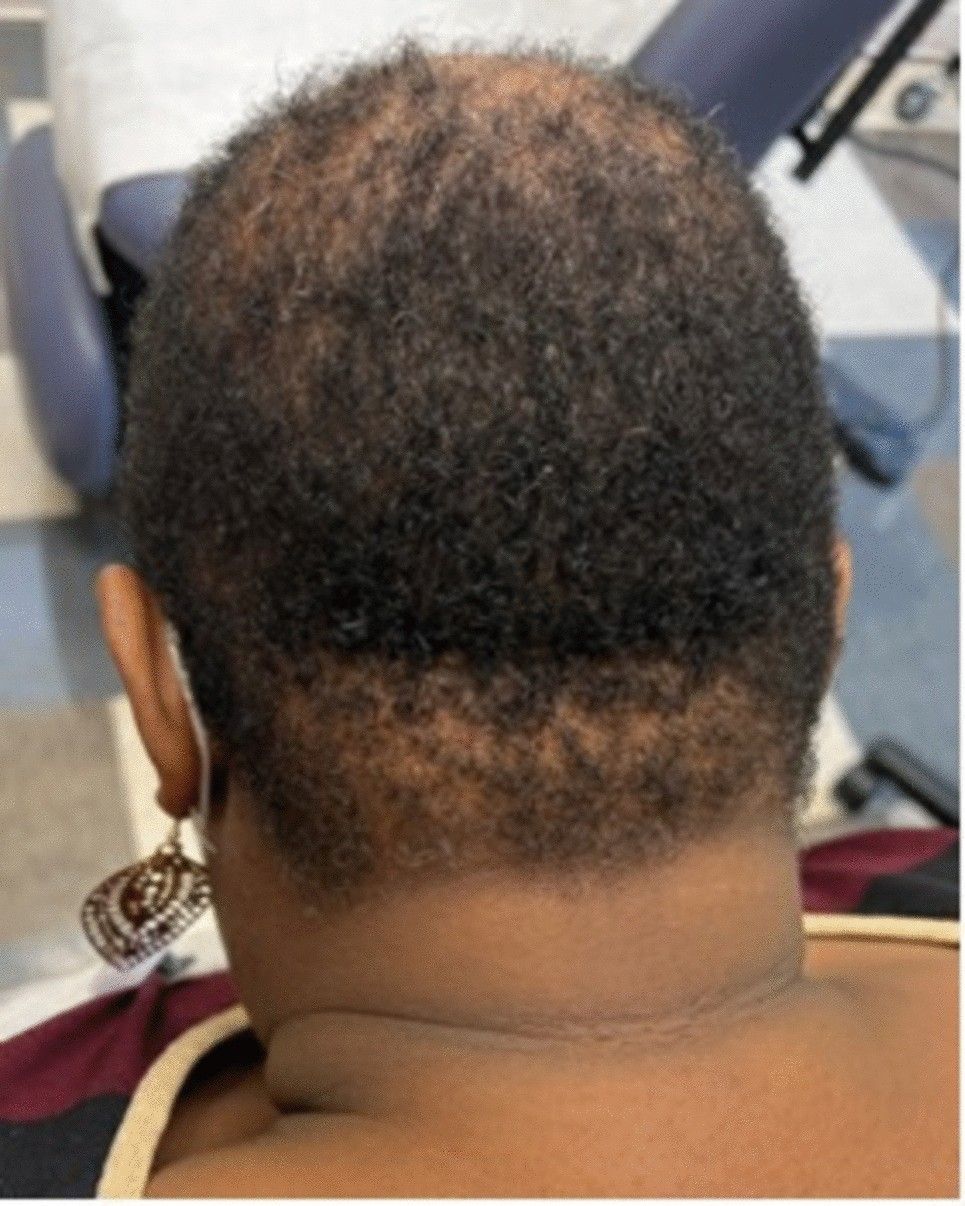
Traction alopecia develops gradually from repeated tension on the hairline, typically from tight hairstyles such as braids or ponytails. It is often reversible if the mechanical stress is removed early. Scalp conditions such as seborrhoeic dermatitis and psoriasis can also cause temporary shedding and inflammation that disrupts the hair cycle. These are worth treating in their own right, not just as a secondary concern.
When you see your GP, bring date-stamped photos showing the progression of your hair loss, a list of all current medications (including supplements), and a note of any relevant family history. This significantly shortens the diagnostic process.
How does a GP diagnose hair loss, and when should you seek help?
Most hair loss is diagnosed through a clinical history and scalp examination. Blood tests are not routinely required for classic male pattern baldness; they are ordered when the presentation is atypical, rapid, or accompanied by other symptoms.
A GP will typically ask about:
- When the loss started and how quickly it has progressed
- Recent illness, surgery, significant stress, or major weight change
- Current medications and supplements
- Family history of hair loss on both sides
- Diet and any recent nutritional changes
If the presentation suggests a reversible cause, targeted blood tests may include ferritin and iron studies, thyroid function, and Vitamin D where clinically indicated. A full hormonal panel is not standard for typical pattern loss.
When to seek prompt review:
- Sudden or rapidly progressive loss over weeks rather than months
- Patchy loss with smooth, well-defined borders (possible alopecia areata)
- Hair loss extending to the beard, eyebrows, or other body areas
- Scalp pain, burning, or visible scarring alongside hair loss
- Hair loss accompanied by fatigue, weight change, or other systemic symptoms
If hair loss involves the beard or eyebrows, or is diffuse rather than following a recognisable pattern, clinicians will consider non-pattern causes and investigate further. Referral to a dermatologist is appropriate when the diagnosis is uncertain, the condition is progressing despite treatment, or scarring alopecia is suspected.
Is your hair loss temporary or permanent?
The single most useful rule: hair loss that follows the classic frontal recession and crown-thinning pattern of androgenetic alopecia is almost certainly permanent without intervention. Diffuse shedding that started recently, particularly after a clear trigger, is more likely to be temporary.
A practical decision flow:
- Rapid onset over weeks, diffuse shedding: suspect telogen effluvium; look for a trigger two to four months prior
- Smooth, discrete patches: consider alopecia areata; see a GP
- Classic frontal and crown recession: androgenetic alopecia; permanent but treatable
- Hairline recession at temples only, linked to tight hairstyles: traction alopecia; potentially reversible
One important point on outcomes: most treatments aim to maintain existing hair or slow further loss rather than fully restore a youthful hairline. This is not a failure of treatment; it reflects the biology of follicle miniaturisation. Men who start treatment early, before significant follicle loss has occurred, tend to see the best results. Waiting until loss is advanced limits what any treatment can achieve.
Track your hair loss with monthly date-stamped photos taken under consistent lighting. Changes that feel dramatic day-to-day often look more gradual in a photo series, and this evidence is genuinely useful at a GP or clinic appointment.
What treatments are available for male hair loss in the UK?
| Treatment | How it works | Typical effect | UK access |
|---|---|---|---|
| Minoxidil (topical/oral) | Prolongs anagen phase, increases follicle size | Slows loss, modest regrowth in some men | OTC (topical); GP/private for oral |
| Finasteride (oral) | Inhibits 5-alpha reductase, reduces DHT | Slows loss, maintains density | Prescription only; NHS or private |
| PRP (Platelet Rich Plasma) | Growth factors from own blood stimulate follicles | May support density; adjunct to medical treatment | Private clinics |
| Scalp Micropigmentation (SMP) | Cosmetic tattooing to replicate follicle appearance | Aesthetic improvement, not regrowth | Private clinics |
| Hair transplant (FUE/DHI) | Relocates DHT-resistant follicles to thinning areas | Permanent natural-looking results | Private clinics |
NHS guidance confirms that finasteride and minoxidil are the established first-line medical options for male pattern hair loss, and both should be discussed with a GP before starting. The British Association of Dermatologists supports this approach and provides clinical guidance for practitioners managing hair loss in primary and secondary care.
Finasteride works by inhibiting the enzyme 5-alpha reductase, which converts testosterone to DHT. It is effective at slowing androgenetic alopecia in most men who take it consistently, but it carries a small risk of sexual side effects that should be discussed with a prescribing clinician before starting. Minoxidil is available over the counter as a topical solution or foam; oral minoxidil is available on private prescription and may suit men who find topical application inconvenient.
Before choosing a provider, check the registration of the named clinician and the treatment location. Ask for a written treatment plan, the full cost and details of follow-up care.
A note on realistic expectations: clinical guidance from the Primary Care Dermatology Society emphasises that stabilising loss and improving quality of life are the primary goals of treatment. Full restoration is not a realistic expectation from medical therapy alone; surgical options can achieve more significant density restoration, but only in suitable candidates with stable donor hair.
Practical steps to protect your hair and scalp
You cannot prevent androgenetic alopecia if you are genetically predisposed, but you can reduce avoidable loss and support the effectiveness of any treatment you are using.
Do:
- Eat a balanced diet with adequate protein, iron, and zinc
- Address scalp conditions such as dandruff or seborrhoeic dermatitis promptly
- Manage stress where possible; chronic stress is a recognised telogen effluvium trigger
- Use gentle shampoos and avoid excessive heat styling
- Seek early assessment if you notice changes; earlier treatment consistently produces better outcomes
Avoid:
- Tight hairstyles that place sustained tension on the hairline
- Crash dieting or very low-calorie diets, which can trigger diffuse shedding
- Delaying a GP visit because you assume the loss is “just genetic”
If you suspect a nutritional cause, ask your GP for a ferritin test before self-supplementing with iron. Excess iron supplementation without confirmed deficiency carries its own risks. Zinc and Vitamin D are worth testing if your diet is restricted or you have other risk factors. For practical guidance on preventing further thinning, early action consistently makes the most difference.
Keep a simple hair-shedding diary for four weeks: note daily shed counts (from the shower or pillow), any new medications, illness, or dietary changes. This gives a clinician far more to work with than a general description of “a lot of hair falling out.”
UK resources and how to check a clinic’s credentials
Knowing where to find reliable information matters as much as knowing what to look for. These are the most authoritative UK sources:
- NHS (nhs.uk/symptoms/hair-loss): Clear patient-facing guidance on causes, when to see a GP, and treatment options. The starting point for most men.
- British Association of Dermatologists (bad.org.uk): Clinical guidance and patient information leaflets on specific conditions including alopecia areata and androgenetic alopecia.
- NICE Clinical Knowledge Summaries (cks.nice.org.uk): Detailed clinical guidance used by GPs; the most rigorous UK-specific evidence base for diagnosis and treatment decisions.
- Alopecia UK (alopecia.org.uk): Patient support organisation with condition-specific resources, particularly useful for men dealing with alopecia areata or extensive hair loss.
What to check before choosing a clinic
If you are considering a private clinic for surgical or procedural treatment, verify the following before committing:
- Surgeon is on the GMC register (searchable at gmc-uk.org)
- Clinic holds CQC registration (England) or HIS registration (Scotland)
- Before-and-after galleries show real, documented patient outcomes rather than stock imagery
- The consultation covers your full medical history, realistic outcome expectations, and a written treatment plan
- Consent procedures are clearly documented and you are given time to consider before proceeding
Useful sources
- NHS: Hair loss — Patient-facing guidance on causes, when to see a GP, and an overview of treatment options. The most accessible starting point for men in the UK.
- NICE Clinical Knowledge Summaries: Male pattern hair loss — The clinical evidence base used by UK GPs; covers diagnosis, investigation, and treatment in detail.
- British Association of Dermatologists — Professional body for UK dermatologists; publishes patient information leaflets and clinical guidelines on alopecia conditions.
- Alopecia UK — Patient support organisation with condition-specific resources, particularly for alopecia areata and extensive hair loss.
- Skin Health Info (Skinhealthinfo.org.uk) — Produced by the British Association of Dermatologists; detailed patient information on androgenetic alopecia including genetics and treatment.
FAQ
What are the main causes of hair loss in men?
Androgenetic alopecia (male pattern baldness) is the most common cause, affecting around 50% of men over 50 in the UK. Other causes include telogen effluvium, alopecia areata, nutritional deficiencies, scalp conditions, and certain medications.
What is the best treatment for male hair loss in the UK?
Finasteride and minoxidil are the established first-line treatments recommended by NHS guidance and the British Association of Dermatologists. Both should be discussed with a GP before starting, as suitability and access vary.
Can stress cause hair loss in men?
Yes. Significant physical or emotional stress is a recognised trigger for telogen effluvium, which causes diffuse shedding typically two to four months after the stressful event. This type of hair loss is usually temporary and resolves once the trigger is removed.
Can you regrow hair once it has been lost?
It depends on the cause. Hair lost through telogen effluvium, nutritional deficiency, or scalp conditions usually regrows once the underlying issue is treated. Hair lost through androgenetic alopecia involves permanent follicle miniaturisation; medical treatments can slow further loss, while surgical transplantation can restore density in suitable candidates.
How do I know if my hair loss needs a GP appointment?
See your GP if your hair loss is sudden, patchy, spreading beyond the scalp, accompanied by other symptoms, or causing you distress. Classic gradual frontal and crown recession in a man with a family history is likely androgenetic alopecia, but early assessment still improves treatment outcomes.
Dr Harpreet Kalra
Newcastle Hair Transplant Clinic